Exercise Physiology and Myotherapy is coming to Ballarat Sports Medicine

Grant McKechnie BEd(PE), DipM(RM), AdDip(Myo), GradDipHSc(ExRehab), MAppSci(Research), ProfCert(Pain NeuroSci/Edu)

Ballarat Sports Medicine is very excited to announce that Grant McKechnie is joining the team of practitioners consulting at Novar!

Grant is Ballarat’s (and possibly Australia’s) most experienced clinical exercise physiologist. Over a 24 year career in both public and private settings, he has an enormous depth and breadth of experience in rehabilitation, strength and conditioning, myotherapy and pain management. 

Having his expertise on site expands the ability to manage sports and other musculoskeletal injuries from start to finish. From getting the correct diagnosis, through our sports medicine team, surgery if needed, physiotherapy and now another element to the high-end rehabilitation and return to activity, the team can help patients at all steps in the process. 

Areas of Interest:

Grant began practicing in September 2000, working at The University of Ballarat’s (now Federation University Australia) – UniSports Exercise Rehabilitation Centre.  Whilst there he continued to study, gaining his Master of Applied Science as well as various soft tissue qualifications including Myotherapy. Grant was a lecturer in both undergraduate and Master’s programs; with a particular focus on the Masters of Rehabilitation anatomy program.

Since this time, Grant has written and delivered entire courses in Remedial massage and Myotherapy for the University of Ballarat and private colleges in Melbourne. These courses have a particular focus on the care, prevention and rehabilitation of musculoskeletal injuries.

Grant commenced Ballarat Sports & Exercise Rehabilitation Centre 2005, a multi-disciplinary clinic, which included Exercise Physiology and Myotherapy. Grant delivered in-house rehabilitation and professional development education for musculoskeletal, metabolic, neurological and cardiovascular conditions. 

Topics included

Grant has been successfully treating many conditions with a bias toward chronic pain and recalcitrant conditions that haven’t responded to standard methods of treatment. He continues to develop his practice and knowledge, currently pursuing the field of neurology and neuroplastic approaches to rehabilitation.

Grant is active in professional development for Myotherapy Association Australia where he has been the Chair of the project steering committee for the reaccreditation of the Myotherapy training package twice and was on the discussion panel for the direction of myotherapy at the biannual conference. Grant has presented at the Commonwealth International Sports Conference, as well as many various guest lecturer roles, including presenting at the Primary Health Network educating doctors on topics such as sarcopenia and exercise, and the neuroplasticity of pain. 

Grant has worked with both professional and semi-professional athletes. This has included development and implementation  of

The athletes include; Olympic and Commonwealth Games representatives in various sports, Professional Mixed Martial Arts & Brazilian Jujitsu fighters, Motocross, Cyclists, Ultra-distance and Marathon runners, Ironman and Triathlon, Rowing, Tennis, Badminton, Race-walking and AFL football. He has worked as a rehabilitation therapist at the North Ballarat Roosters VFL in 1999 and 2000, and has been a professional injury consultant for the AFL.

In 2017 Grant was awarded the Myotherapy Australia’s Tony Moynihan award regarding excellence in the field of myotherapy. In 2018 he presented at the international Neuro-Impulse Protocol symposium on how exercise can correct neurological dysafferentation.

In 2020 Grant was a recipient of a scholarship from the Pain Revolution, to study Pain Neuroscience and Pain Education at the University of South Australia. Grant has completed this study and is now forming the Pain Revolution’s  local pain collective for Ballarat and surrounding districts. The collective is to educate professionals and the community on contemporary pain neuroscience and how to better address the growing issue of  persistent pain in the community.

Grant will be consulting at NOVAR, 109 Webster Street Lake Wendouree, from Wednesday to Friday, commencing 12/04/2023, and alternate Saturday mornings from 22/04/2023. 

Bookings can be made on-line at

Or call

Ballarat Sports Medicine’s New Registrar

Ballarat Sports Medicine has a new Sport and Exercise Medicine registrar, Dr Jai Sharma.  Jai manages to combine many passions in life – medicine, sport and exercise.  He has a passion for local cricket, running, cycling and enjoys a good coffee.

A Ballarat boy himself, Jai moved to the UK to acquire his medical degree (University of Liverpool 2015) and gain valuable experience working in the NHS before returning home to Victoria.


He has extensive experience in many hospital settings in particular orthopaedic surgery, emergency medicine, general practice and general medicine. Regarding sports, he has worked as team doctor for North Melbourne and Frankston VFL teams,  with AFLW  as the concussion doctor and coverage of cycling events. Jai has also completed a Master’s degree in Sports Medicine (University of Queensland 2021).


Growing up and going to school in Ballarat gives Jai a unique perspective of the local area and he is keen to engage with the local community and other health care professionals involved in your care to provide the best possible management for you.

Jai will be available for appointments in mid-February.

Ballarat Sports Medicine has a new physiotherapist

Simon Lewis has recently joined both Luke Blunden and Peta Johnston as a physiotherapist Ballarat Sports Medicine, increasing physiotherapy availability. Simon’s journey towards physiotherapy began back in high school with an intense interest in athletics and sport. He has since completed a Certificate IV in Fitness, Bachelor of Health and Physical Education (Deakin University)
and a Bachelor of Physiotherapy Honours (Australian Catholic University Ballarat). He has worked as a personal trainer, teacher, and physiotherapist across multiple sites in Ballarat, Melbourne, and the Grampians region.

Treating the whole person is a core value of Simon’s and this is reflected in the coaching approach that he uses. Simon has a particular interest in treating children and teens as well as older adults. His passion lies in helping people not only recover from injury but to thrive and improve all aspects of their lives. Simon has completed further study in the areas of paediatric physical activity, psychological informed practice, behaviour change, and pain education. When not working Simon enjoys spending time with his wife and two daughters, going for a hike, or hitting the gym.

Appointments are now available for Simon at: 

Obesity and hip replacement

A new study published demonstrates hip replacement surgery fixes pain and improves walking both in obese and non obese patients, but the obese group are more likely to need walking aids at ten years.

Continue reading

Australian National Joint Replacement Registry Report 2022

Australia has been leading the world with its National Joint Replacement Registry since 2000, with every joint replacement and its long term outcome being followed.

Key issues identified this year include:

  1. The registry is now tracking the outcome of 1.8 million joint replacements.
  2. 2021 saw 52,787 hip replacements, 68,466 knee replacements, and 8,733 shoulder replacements.
  3. As a result of COVID, some 19,500 people have not had a joint replacement that in normal times should have occurred. This was predominantly in the public sector, with a 14.9% reduction compared with 2019.

Implants that were implanted 10 years ago, still being used, have a 4.4% ten-year failure for hips, and 4.7% for knees.  Young patients under 55 having knee replacement are the biggest risk.

Various designs and surgical approaches have been advocated to improve results. Highly cross-linked polyethylene (XLPE) is a proven winner, but dual mobility, and constrained liners, have not improved outcomes for primary hip replacement.

Anterior surgical approach in the Australian Registry has a lower dislocation rate, but the overall revision rate not changed.  It seems currently any dislocation improvement is offset by an increased risk in fracture & loosening.  

Total hip replacement for fracture (instead of bipolar) has become more common, with a 10-year revision rate of 6.9% vs 5.3% for the bipolars.  That difference is obvious for the older patients over 70, but not very different for the younger ones.

Hip resurfacing in men, with a femoral head size of 50mm or greater still has a place.

Partial knee replacement has diminished to 5.6% of knee replacements, the robotic Restoris (Mako) doesn’t seem better than the ZUK, or Persona.

Some designs have been identified as having a higher-than-expected revision rate, fortunately we have not routinely used these.

Platelet Rick Plasma (PRP) Injections

What is plasma and what are platelets?

Plasma is the liquid portion of whole blood. It is composed largely of water and proteins, and it provides a medium for red blood cells, white blood cells and platelets to circulate through the body. Platelets, also called thrombocytes, are blood cells that cause blood clots and other necessary growth healing functions.

Platelet activation plays a key role in the body’s natural healing process.

What is platelet-rich plasma (PRP) and what are PRP injections?

Platelet-rich plasma (PRP) is a growth factor rich medium that is developed from the patient’s blood. It is not synthetic.  PRP therapy uses injections of a concentration of a patient’s own platelets to accelerate the healing of injured tendons, ligaments, muscles and joints. In this way, PRP injections use each individual patient’s own healing system to improve musculoskeletal problems.

PRP injections are prepared by taking anywhere from one to a few tubes of your own blood and running it through a centrifuge to concentrate the platelets. These activated platelets are then injected directly into your injured or diseased body tissue. This releases growth factors that stimulate and increase the number of reparative cells your body produces.

Research has shown PRP to be effective in the management of early osteoarthritis (joint degeneration) and some tendon injuries.

How are PRP injections done? What is involved?

PRP therapy involves one (for tendons) or two injections (for joints) into the injured area a fortnight apart. On each occasion the patient will be required to donate blood for generation of the PRP.  Injections are done under sterile conditions, with local anaesthetic and using ultrasound guidance.  Each procedure will take approximately 30 minutes.

We published a research paper in 2022 showing that two injections of PRP for knee osteoarthritis reduces symptoms in the majority of cases. We also showed that three injections (or more) were not more effective than two.

What do I need to do before my injections?

Patients are required to cease taking anti-inflammatory tablets one week prior to the PRP procedure.  Patients taking regular aspirin should continue to take this.

What do I need to do after my injections?

It is recommended that someone drive the patient home after an injection due to some potential residual effects of the local anaesthetic or discomfort from the procedure. Depending on the structure injected, the patient may need to offload the area for a period. 

Patients undergoing PRP injections should also be actively involved in a supervised rehabilitation program.  In some instances, the patient may need to stop exercise for a period and resume after medical review.

Risks

In general, adverse outcomes from PRP injections are rare, but they may include:

Bleeding/Bruising/Infection

To reduce chance of infection all injections are done under sterile conditions using ultrasound guidance for accuracy. PRP has natural anti-bacterial properties that reduce chance of infection.

Pain/Discomfort

Injections can be uncomfortable. In all cases, local anaesthetic is used. Patients are encouraged to use simple analgesia (Panadol/Panadeine) as required after the procedure and icing can be very helpful.  If necessary, the doctor can provide a prescription for Panadeine Forte. Much of the post procedure discomfort can be addressed by closely following any post procedure instructions.

Contra-Indications

PRP injections are generally very safe, but are contra-indicated in the following conditions:

  • Pregnancy
  • Cancer
  • Some bleeding disorders

More information/evidence for PRP?

The use of intra‐articular platelet rich plasma for the symptomatic management of osteoarthritis of the knee: a pilot study. Sibillin O, Mitchell D, Harris G et al. ANZ J Surg (2022) doi:10.1111/ans.17565

Rehabilitation vs Surgical Reconstruction for Non-acute Anterior Cruciate Ligament Injury

Anterior cruciate ligament (ACL) tears are among the most common and costly injuries. Both surgery and rehabilitation options are available to the patient. There is a longstanding difference of opinion as to which is the better strategy for non-acute ACL injuries. This study aimed to compare patient outcome and cost effectiveness for both surgery and rehabilitation.

The study recruited 316 patients with non-acute ACL injuries and persistent instability. This cohort was randomized onto either immediate surgery or rehabilitation. Several outcomes were assessed. Primarily the Knee Injury and Osteoarthritis Outcome Score was compared, but other factors that were compared included quality of life measures, the Tegner activity score (measures activity ranging from zero – disability due to knee injury; to 10 – elite level sport stability), resource use, complications, and patient satisfaction. All patients were followed up at 18 months. The study results determined that both groups showed improvement, though, patients who received immediate surgery had significantly better knee function, pain, patient satisfaction, and Tegner activity scores compared to the rehabilitation group. Cost effectiveness was 72% more likely in patients having had surgery compared to those who had rehabilitation.

For further information on this study, see https://myorthoevidence.com/AceReport/Report/14922

Reference:
OrthoEvidence. Rehabilitation vs. Surgical Reconstruction for Non-acute Anterior Cruciate Ligament Injury. ACE Report. 2022;285(1):1.

NOVAR Musculoskeletal Research Institute (NMRI)

We have a new donation portal

Your Tax-Deductible donations of support are very welcome

Ballarat OSM and NOVAR Specialist Healthcare work closely with NMRI, a non-for-profit clinical research, training, and education institute based in Ballarat. Through collaboration with the community, we seek to improve the lives of patients with musculoskeletal conditions and diseases.  Our aim is to enhance the understanding and healthcare of musculoskeletal disease through published clinical and non-clinical research, by collecting and collating data utilised for information dissemination through publishing high quality articles in reputable journals and enhancing cooperation.

You can help by participating in our patient outcomes research program, and by making a tax-deductible donation to support the research institute.

No bones about it, we can’t do it without your support.

Our Vision

Masters of responsible research and innovation, driving collegiality and improvement in musculoskeletal disease healthcare.

Our Mission

Innovative patient focused research institute that engages and enriches the community, through improved musculoskeletal healthcare outcomes via strong commitment to excellence in the field of traumatic and degenerative musculoskeletal disease.

Range-of-Motion Exercises for Arthritis

Stretches and range-of-motion exercises aim to improve the mobility and flexibility of your joints. To increase your range of motion, move a joint as far as it can go and then try to push a little farther. These exercises can be done any time, even when your joints are painful, as long as you do them gently.

Here are four range-of-motion exercises that you can do at home.


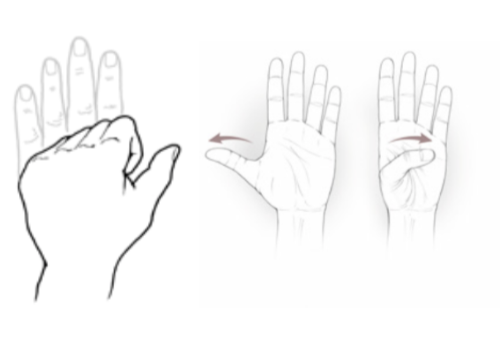
Arthritis Hand Exercise

Hand

Open your hand, holding the fingers straight. Bend the middle finger joints. Next, touch your fingertips to the top of your palm. Open your hand. Repeat 10 times with each hand. Next, reach your thumb across your hand to touch the base of your little finger. Stretch your thumb back out. Repeat 10 times.

Shoulder

Lie on your back with your hands at your sides. Raise one arm slowly over your head, keeping your arm close to your ear and your elbow straight. Return your arm to your side. Repeat with the other arm. Repeat 10 times.

Knee

Sit in a chair that is high enough for you to swing your legs. Keep your thighs on the seat and straighten out one leg. Hold for a few seconds. Then bend your knee and bring your foot as far back as possible. Repeat with the other leg. Repeat 10 times.

ArthritisExerciese_4

Hip

Lie on your back, legs straight and about 6 inches apart. Point your toes toward the ceiling. Slide one leg out to the side and then back to its original position. Try to keep your toes pointed up the whole time. Repeat 10 times with each leg.

Our team of Physiotherapists, Sport & Exercise Medicine physicians and Orthopaedic Surgeons will be able to specifically advise you of your capacity and frequency for undertaking these exercises based on your condition.

To learn more about how exercise can help alleviate the symptoms of osteoarthritis, check out Living Well with Osteoarthritis, a Special Health Report from Harvard Medical School.